TL;DR: Every surgical facelift leaves a scar; the real choices are where it goes, how long it is, and what you give up to make it shorter. A 2024 scoping review of 49 studies found low scar-complication rates for every published incision design — and could not say that any one design is superior, because the studies measure scars in incompatible ways. What the evidence does show: short-scar lifts such as the MACS lift produced aesthetic results and complication rates comparable to deeper SMAS lifts in a 2026 meta-analysis of 286 patients, with shorter operating times; endoscopic "hidden-incision" lifts have been reported in series of 393 and 600 patients without permanent nerve injury, but with touch-up rates of up to 4.8% and a learning curve; and the two tell-tale signs of a facelift — a shifted temple hairline and the "pixie ear" (seen in about 5% of cases in one review) — are largely decided by incision planning, not by the healing. Below: the techniques, what each trades away, what surgeons publishing on Asian patients do, and six questions to ask. Medical Korea Service is a Registered Facilitator for International Patients (Seoul Metropolitan Government, Reg. No. A-2014-01-01-1414, registered 23 July 2014).
Why the scar question is really three questions
Patients usually ask one thing — "will people see it?" — but the answer depends on three decisions the surgeon makes.
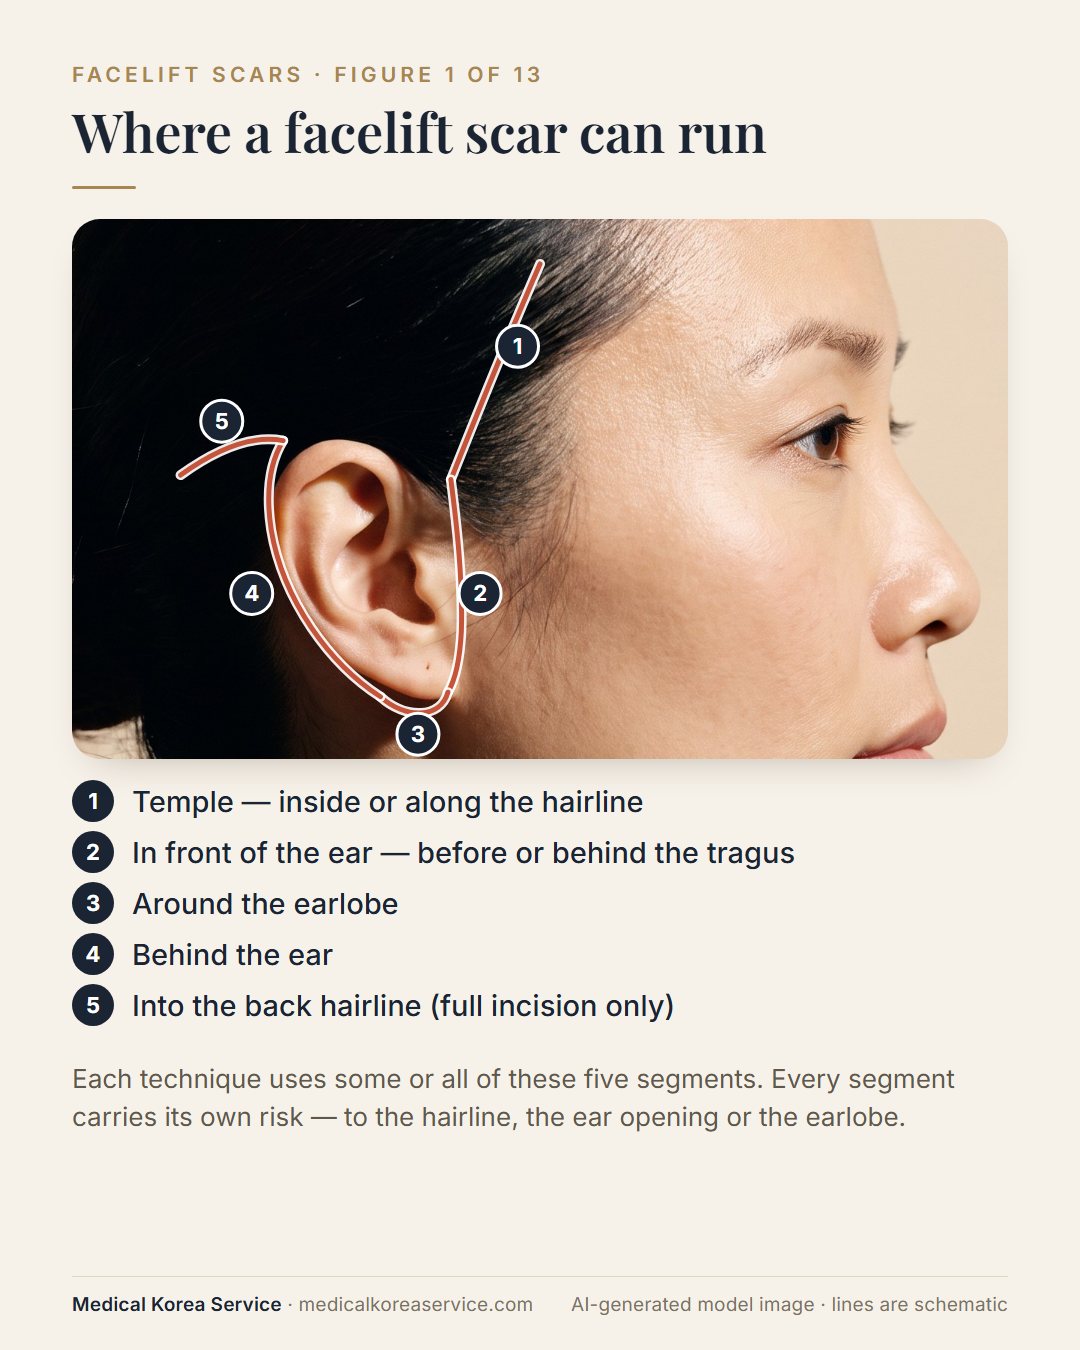
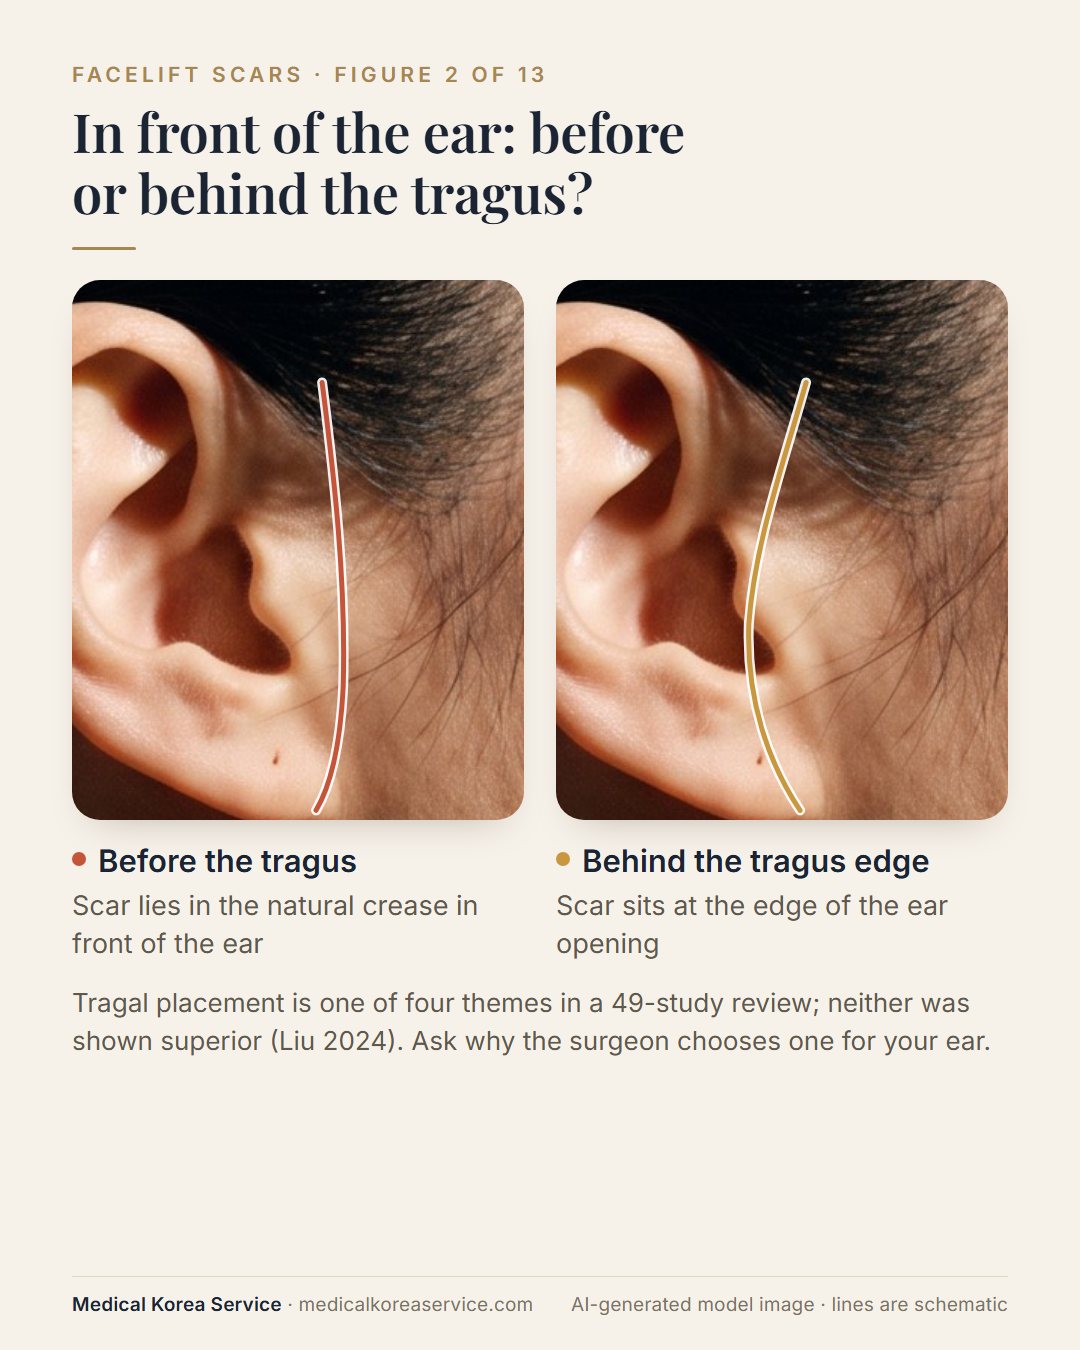
Where the incision runs. A standard facelift incision starts in or along the temple hairline, runs down in front of the ear (either in the natural crease in front of the small cartilage flap called the tragus, or just behind its edge), turns around the earlobe, and continues up behind the ear and sometimes into the hair at the back of the scalp. Each segment carries its own risk — to the hairline, the ear opening or the earlobe.
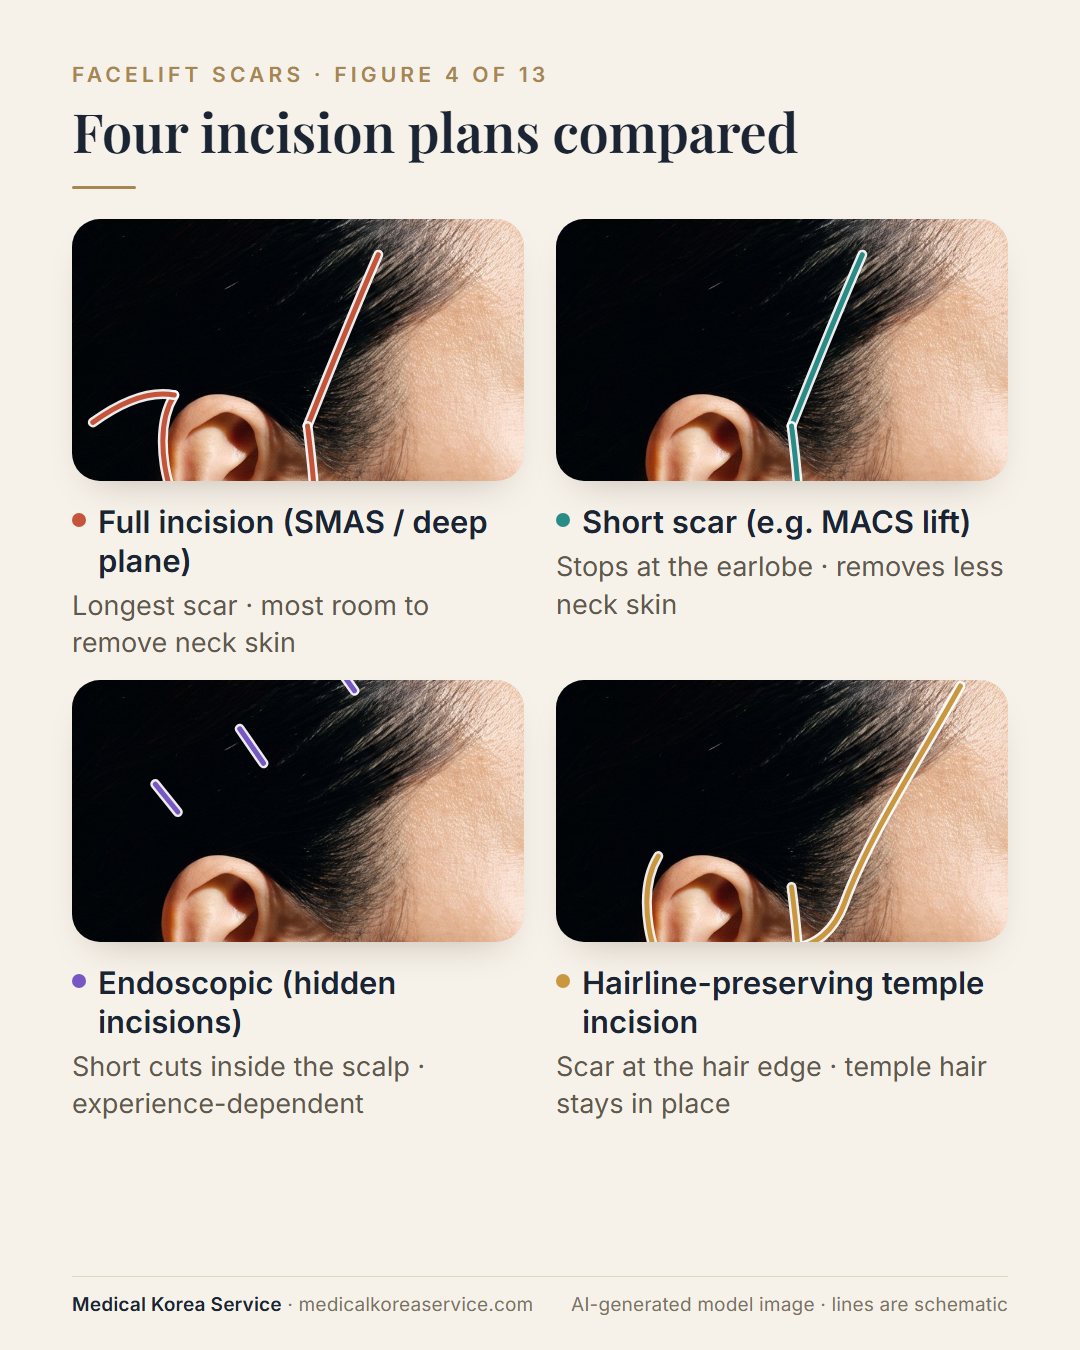
How long it is. "Short-scar" techniques stop the incision at the earlobe or just behind it, leaving out the segment behind the ear and into the back hairline. The trade-off, discussed below, is how much loose neck skin can be removed.
How much tension it carries. A scar under tension widens, thickens or drags on the ear, which is why the deeper tissues should carry the lift and the skin be closed without pulling. A review of facial rejuvenation in non-Caucasian patients lists "planning careful incisions to be closed under no tension" as one of the core principles (Sykes & Nolen, Facial Plast Surg Clin North Am 2014).
According to PubMed, the most complete overview of the question is a 2024 scoping review of rhytidectomy incision techniques and scar outcomes (Liu et al., Facial Plast Surg 2024). The authors included 49 studies and grouped them into four themes: temporal incision placement, tragal incision placement, management of the earlobe, and the design of the incision behind the ear. Their conclusion is worth quoting in substance: every technique described reported low rates of scar complications, but it was not possible to say which is superior, because the studies used different outcome measures, designs and follow-up periods.
So any clinic — in Korea or anywhere else — that says its incision "leaves no scar" or is "proven better" is going beyond the evidence. The honest comparison is about trade-offs, not winners.

The main techniques compared
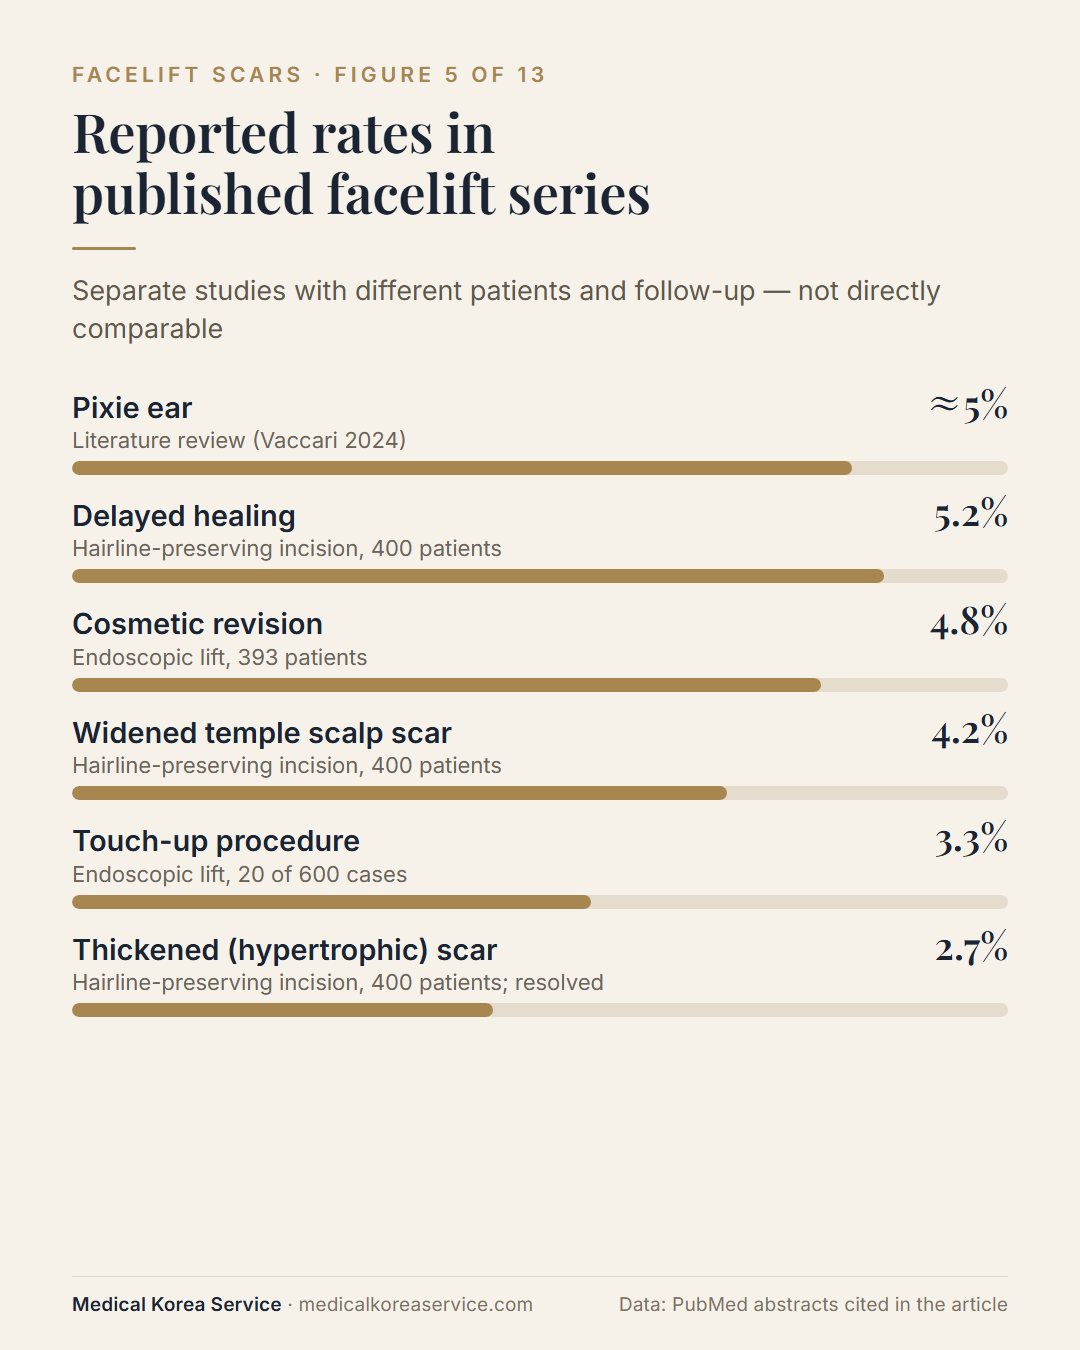
The table summarises the four families of technique you are most likely to be offered, with the published figures we could verify directly from PubMed abstracts. The series are single-surgeon or small-group reports, so read the numbers as "what has been achieved in experienced hands", not as the rate you should expect everywhere.
| Technique | Where the scar goes | What the published series report | What it trades away |
|---|---|---|---|
| Traditional full-incision SMAS or deep-plane facelift | Temple (in or along the hairline), in front of the ear, around the earlobe, behind the ear and into the back hairline | The reference technique; scar-related complications low in the literature but measured inconsistently (49-study review) | Longest scar; most places where the hairline or earlobe can be distorted if tension is poorly managed |
| Short-scar lift (e.g. MACS lift) | Temple and in front of the ear, stopping at or just behind the earlobe | Systematic review of 6 studies, 739 patients: no major complications reported and relatively high satisfaction. Meta-analysis vs deep SMAS lift (286 patients): comparable aesthetic results and complications, significantly shorter operating time | Less room to remove loose skin of the lower neck; best suited to earlier or moderate ageing |
| Endoscopic ("hidden incision") lift | Short incisions inside the scalp above the ear, sometimes a small incision near the ear for the neck | 393 patients (2020–2024): no permanent nerve injury; cosmetic revision 4.8%, mostly in the surgeon's first 100 cases. 600 cases over 22 years: no skin-flap necrosis, no permanent nerve injury, 20 touch-up procedures | Technically demanding and learning-curve dependent; when significant neck skin must be removed, a skin incision is still added |
| Hairline-preserving temple incision (full lift) | Behind or at the edge of the temple hair instead of across it, then the usual path around the ear | 400 women, 12 months: no temple hairline distortion, sideburn irregularity or visible front temple scars; widened temple scalp scars 4.2%, delayed healing 5.2%, thickened (hypertrophic) scars 2.7%, all resolving | A scar at the hair edge relies on hair to hide it; ask how it would sit with your own hair density and styling |
Every figure in the table comes from a study linked in the sections below (PubMed abstracts). These are separate series with different patients and follow-up; the figures are not directly comparable with each other.
Short scar: shorter, but not for every neck
The most studied short-scar technique is the minimal access cranial suspension (MACS) lift, which lifts the tissues vertically with suspension sutures through an incision in front of the ear and at the temple. A systematic review 18 years after its introduction found six studies covering 739 patients, with no major complications reported (Hijkoop et al., J Plast Reconstr Aesthet Surg 2021). A 2026 meta-analysis comparing it with the deep SMAS lift found comparable aesthetic results and complication rates, with a significantly shorter operation (Pandkhahi et al., Medicina 2026) — though it rests on only four studies and 286 patients.
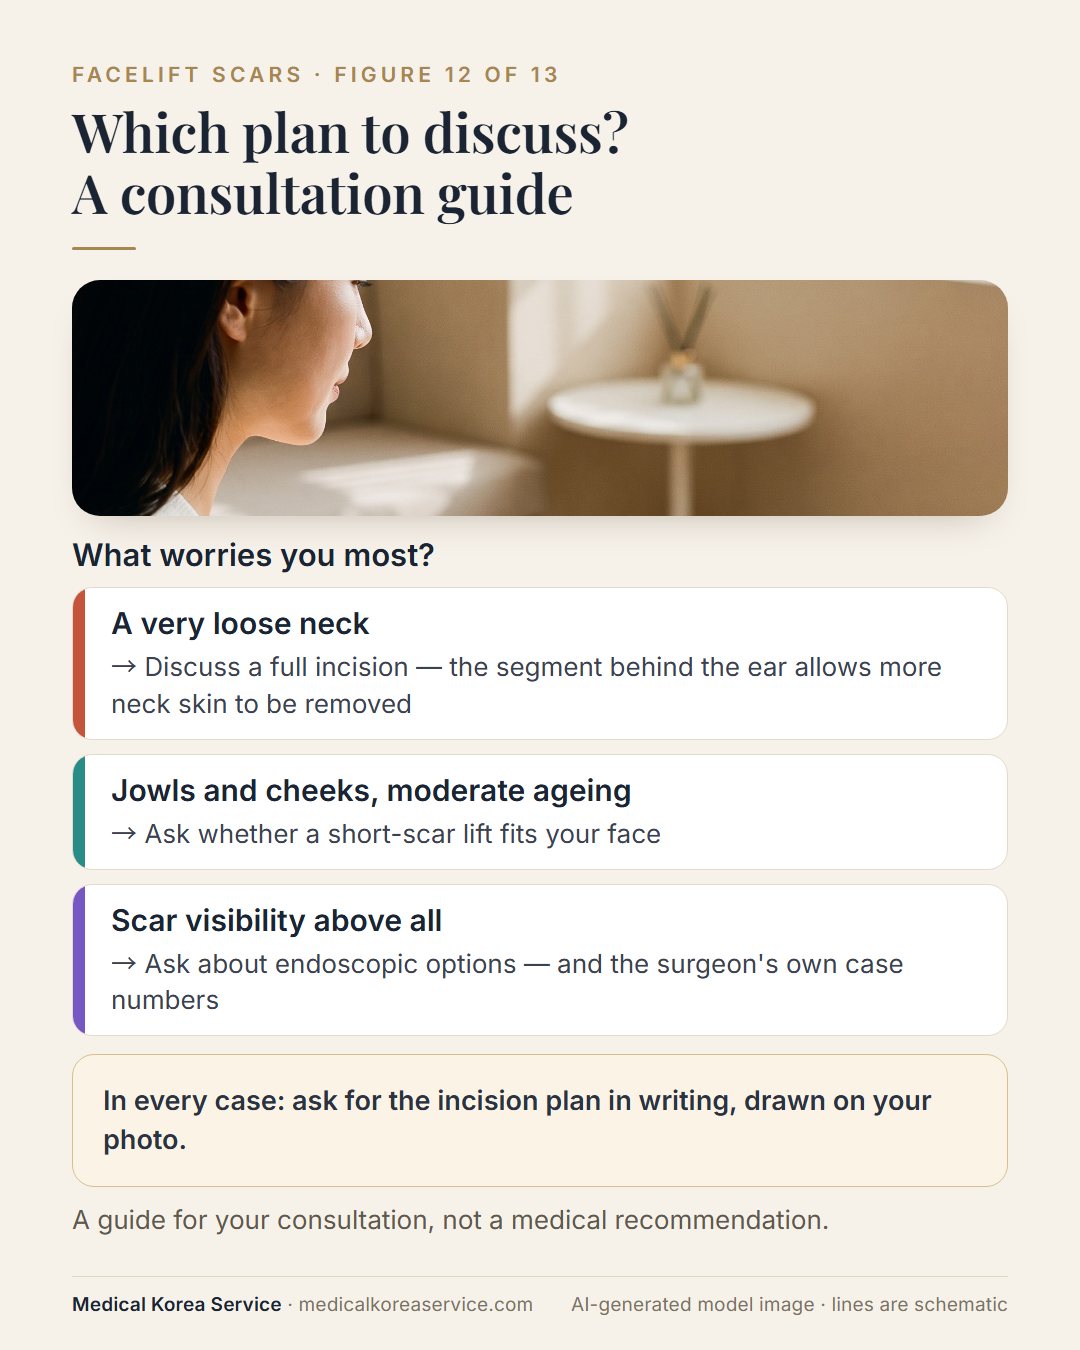
The limit is the neck. Without the incision behind the ear, there is less room to remove excess skin from the lower neck. Surgeons publishing on East Asian patients have also noted that short-scar lifts on their own can leave patients less satisfied with the nasolabial folds, and have described combining techniques to address this (Qiu et al., Plast Reconstr Surg 2021, 20 patients). A shorter scar suits jowls and cheeks better than a loose neck.

Endoscopic: hidden, but experience-dependent
Endoscopic techniques move most of the access into the hair-bearing scalp and use a camera to work in the deep plane. Two large recent series report no permanent nerve injury in 393 patients (Firat, Aesthet Surg J 2025) and none in 600 cases over 22 years, with no skin-flap necrosis (Kao et al., Aesthet Surg J 2024). But the first of those papers also shows the learning curve plainly: most of its 19 cosmetic revisions (4.8%) came from the surgeon's first 100 cases. The useful question is "how many has this surgeon done?"

The two tell-tale signs: the temple hairline and the "pixie ear"
What gives a facelift away is usually not the scar itself but one of two changes it causes.
A shifted temple hairline or sideburn. If skin is pulled upward and backward and the excess is removed from within the temple hair, the hairline and sideburn move with it. Hairline-preserving incisions are designed to prevent this; in the 400-patient series above, none of the patients had temporal hairline distortion at 12 months (Okumuş, Aesthetic Plast Surg 2026). For men, the sideburn is a particular concern, because a pulled-up sideburn looks feminising; surgeons have described specific techniques to keep its width and position (Muller et al., Aesthetic Plast Surg 2026).

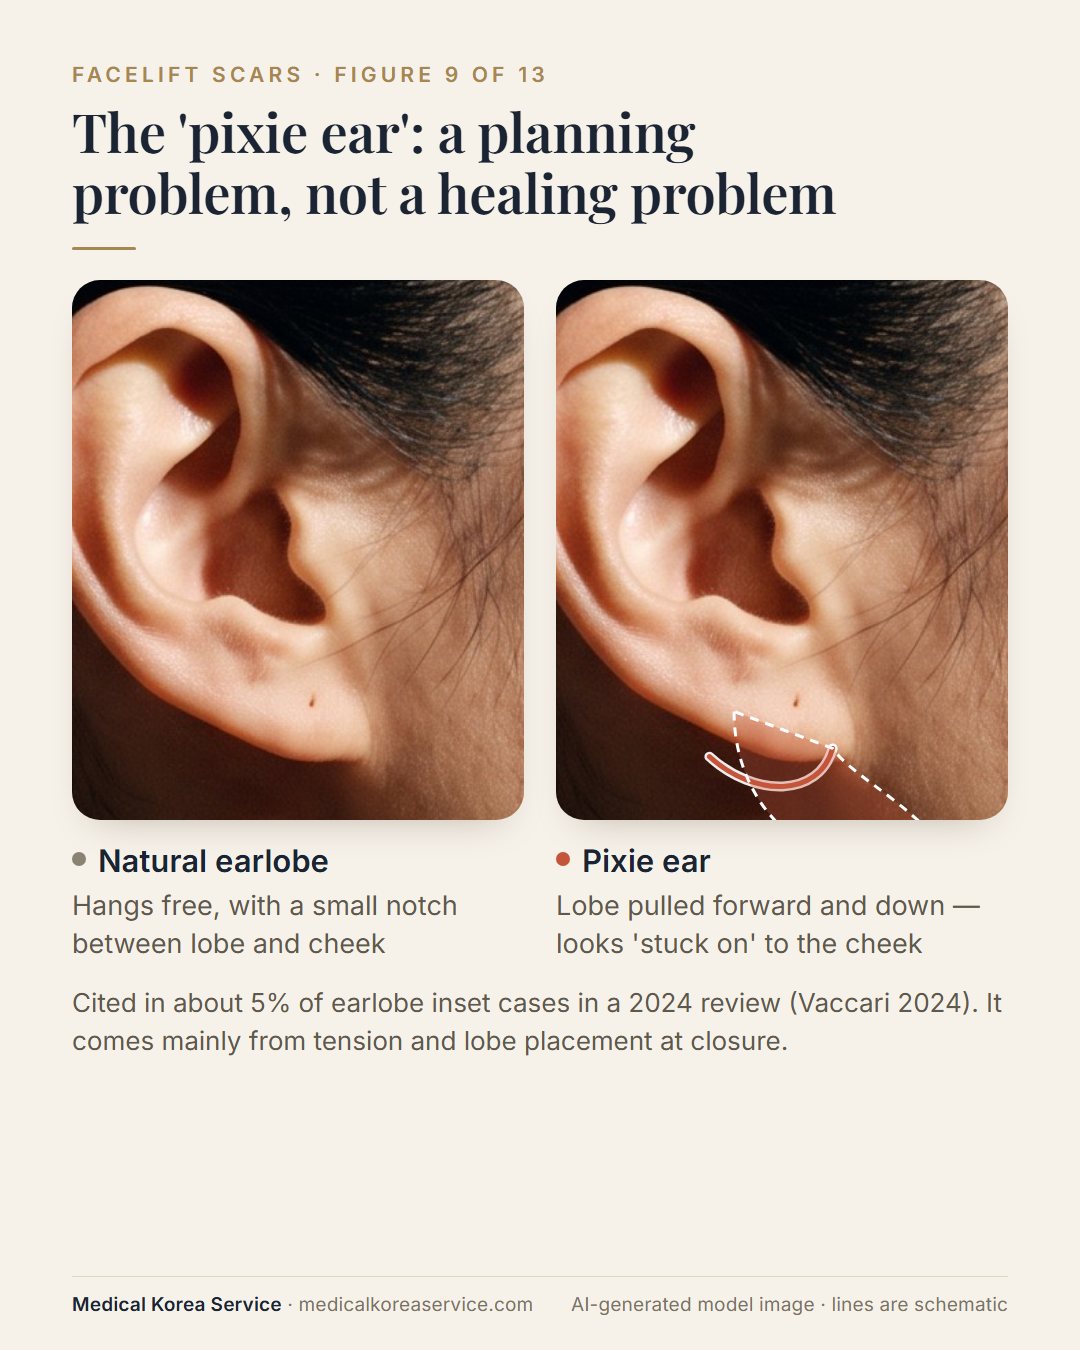
The pixie ear. When the skin flap is closed under tension around the earlobe, the lobe is pulled forward and down and looks "stuck on" to the cheek. A 2024 literature review describes it as a telltale sign of a facelift and cites it in about 5% of earlobe inset cases (Vaccari et al., Surgery 2024). It is a planning problem more than a healing problem: it comes from where and how tightly the lobe is set.
What surgeons publishing on Asian patients do differently
Scar quality in Asian skin is a common worry among the patients who contact us from Singapore and Indonesia, and it is a fair one to raise with any surgeon. We have not found a study that measures facelift scar rates in Asian skin against other skin types directly, so we will not quote a figure. What the literature does show is that surgeons operating on Asian patients have published specific scar-prevention measures and measured them.
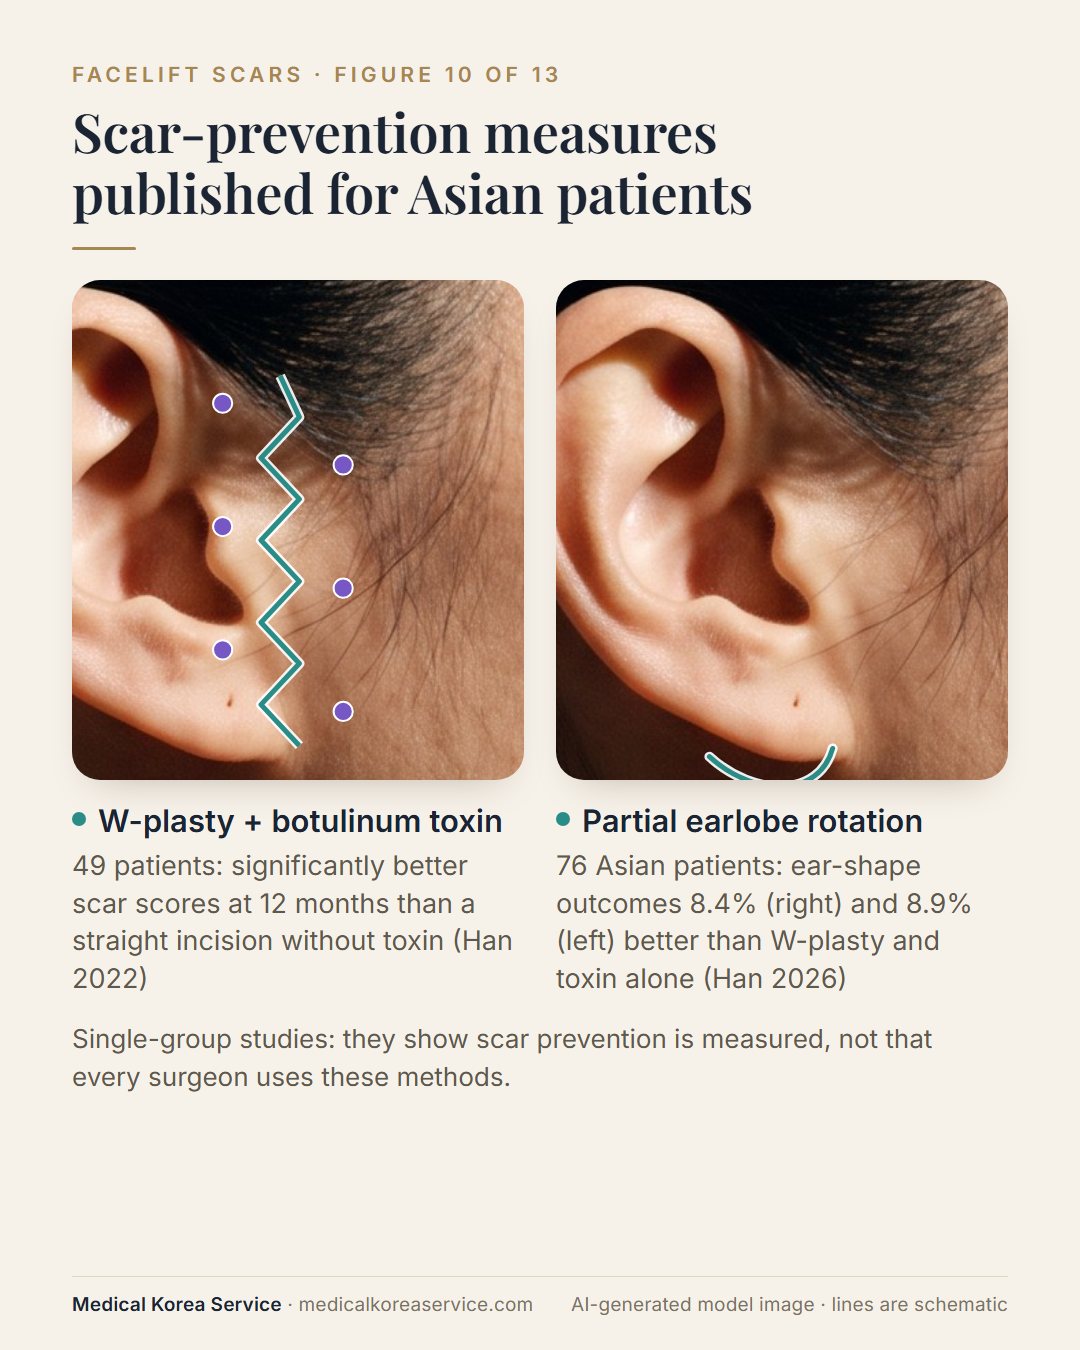
In one comparison of 49 patients undergoing extended deep-plane facelift, patients whose incisions were closed with a zig-zag W-plasty design plus botulinum toxin injected around the incision had significantly better scar scores at 12 months than patients with a straight incision and no toxin (Han, Aesthetic Plast Surg 2022). A later study by the same group in 76 Asian patients found that partially rotating the earlobe during closure improved ear-shape outcomes by 8.4% (right) and 8.9% (left) compared with W-plasty and toxin alone — a statistically significant difference aimed at preventing the pixie ear (Han, Aesthet Surg J 2026).
These are single-group studies: they show that scar prevention in Asian patients is actively measured, not that every surgeon uses these methods. Whether yours does is worth asking.
Three things worth quoting
For Indonesian patients: For Indonesian patients weighing a facelift in Korea, the scar question has no single "best" answer: a 2024 review of 49 studies found low scar-complication rates for every published incision design but could not rank them (Liu et al., 2024). Medical Korea Service (Reg. No. A-2014-01-01-1414) therefore asks the surgeon for the incision plan in writing before any deposit.
For Singapore patients: Singapore patients who want a shorter facelift scar should know the trade-off: in a 2026 meta-analysis of 286 patients, the short-scar MACS lift matched the deep SMAS lift for aesthetic results and complications with a shorter operation (Pandkhahi et al., 2026), but it removes less lower-neck skin. Medical Korea Service (Reg. No. A-2014-01-01-1414) asks which of the two the surgeon recommends for your neck, and why.
For US patients: For US patients comparing "scarless" endoscopic facelifts in Korea, experience is the variable to check: in a 393-patient series, most of the 4.8% cosmetic revisions came from the surgeon's first 100 cases (Firat, 2025). Medical Korea Service (Reg. No. A-2014-01-01-1414) asks surgeons for their own case volume with the technique they propose.
How a facelift scar matures — and what you can do
A new scar is usually pink and slightly firm for the first months and then softens and fades; surgeons commonly judge the final result at around a year, which is also the follow-up point used in most of the studies above.
What is in your control is limited but real: follow the surgeon's written wound-care and suture-removal schedule, avoid smoking (which impairs wound healing), protect the incisions from sun, and report early any area that becomes thick, raised or itchy, because early treatment of a thickening scar is easier than late treatment. For the day-by-day recovery and when it is safe to fly, see our recovery timeline.

Six questions to ask before you book
| Ask the surgeon | Why it matters |
|---|---|
| 1. Draw the incision on a photo of my face — where does it start and end? | Tells you whether it is a full, short-scar or endoscopic plan, and where each segment will sit |
| 2. Is the incision in front of the ear placed before or behind the tragus, and why for my ear? | Tragal placement is one of the four themes the 49-study review found; it affects how natural the ear opening looks |
| 3. How will you keep my temple hairline (and, for men, sideburn) where it is? | A shifted hairline is one of the two tell-tale signs of a facelift |
| 4. How will you set the earlobe to avoid a pixie ear? | The pixie ear is a planning problem; ask what the surgeon does routinely |
| 5. If you propose a short-scar or endoscopic lift, how will it handle my neck — and how many of these have you done? | Short scars remove less neck skin; endoscopic results depend on experience |
| 6. What is the written plan if a scar thickens after I fly home? | Early treatment is easier; you need to know who to contact and what they will do |

How we handle this
When a patient tells us that scars are the main worry, we put these questions to the surgeon before any deposit and ask for the answers in writing, including a marked-up incision plan. If the surgeon recommends a short-scar or endoscopic approach, we ask how it will deal with the neck and what the surgeon's own case numbers are. If a patient's main concern is the neck but a short-scar lift is being proposed, we point out the mismatch. How we choose surgeons in the first place is set out in how we verify Korean plastic surgeons, and why facial anatomy changes the plan for Asian faces is covered in why Asian faces need a different facelift plan.
Frequently asked questions
Is there such a thing as a scarless facelift?
No surgical facelift is scarless. Endoscopic and short-scar techniques shorten or hide the incision but do not remove it. A 2024 review of 49 studies found low scar-complication rates for all published incision designs without being able to rank them.
Is a short-scar (MACS) lift as effective as a full facelift?
In a 2026 meta-analysis of 286 patients, the MACS lift gave aesthetic results and complication rates comparable to the deep SMAS lift, with a shorter operation. It removes less lower-neck skin, so it suits cheeks and jowls with moderate ageing better than a very loose neck.
What is a pixie ear and can it be prevented?
A pixie ear is an earlobe pulled forward and down so that it looks attached to the cheek. A 2024 review cites it in about 5% of earlobe inset cases. It comes mainly from tension and lobe placement at closure, and surgeons have published techniques to prevent it, including partial earlobe rotation in Asian patients.
How long until a facelift scar fades?
Scars are usually pink and firm at first and soften over the following months; most studies judge the result at around 12 months. Protecting the incisions from sun, not smoking and reporting any thickening early all help.
Related reading: Facelift plus eyelids, neck or brow in one operation · Why Asian faces need a different facelift plan · When facial surgery abroad goes wrong: what the case series report · Day-by-day recovery and when it is safe to fly home · Facelift in Korea — how we match you to a verified specialist
This article was prepared by Medical Korea Service as general information for patients considering a facelift. It is not medical advice and does not replace the written instructions of your surgeon, which govern in every case. All study figures are quoted from the peer-reviewed sources linked in the text, retrieved from PubMed abstracts; the studies are separate series and their figures are not directly comparable. No clinic or surgeon is named.